The Rarity and Nonspecific Presentation of GPA and MPA Can Lead to Delays in Diagnosis1
About one-third of patients experience a significant diagnostic delay of more than 6 months1
The information contained in this section of the site is intended for US healthcare professionals only.
Click the appropriate button below.
What You Need to Know About

Anti-neutrophil cytoplasmic autoantibody (ANCA)-associated vasculitis (AAV) is a group of rare diseases that affects small- to medium-sized blood vessels.1,2 Once affected, these blood vessels become inflamed, leading to reduced blood flow and potentially impaired organ function. The exact cause of ANCA-associated vasculitis is currently unknown, but it is believed to be a combination of genetic and environmental factors.1-3
Granulomatosis with polyangiitis (GPA) and microscopic polyangiitis (MPA) are the most common types of AAV and manifest as chronic, progressive autoimmune diseases that impact predominantly small-to-medium blood vessels throughout the body.4-6
GPA: granulomatous inflammation affecting blood vessels involving the upper and lower respiratory tracts and the kidneys; other organs can also be affected7,8
MPA: vasculitis often affecting the kidneys, lungs, and skin7
The American College of Rheumatology/Vasculitis Foundation (ACR/VF) defines active and severe as:
ACTIVE
New, worsening, or persistent clinical signs and/or symptoms attributed to GPA or MPA that are not related to prior damage9
SEVERE
Vasculitis with life- or organ-threatening manifestations9
Approximately 80-90% of patients with ANCA-associated vasculitis present with renal- or other organ-threatening manifestations, which can be considered severe active disease.9,10
Both the humoral pathway and the alternative complement pathway drive inflammatory vascular injury in GPA and MPA.4,5
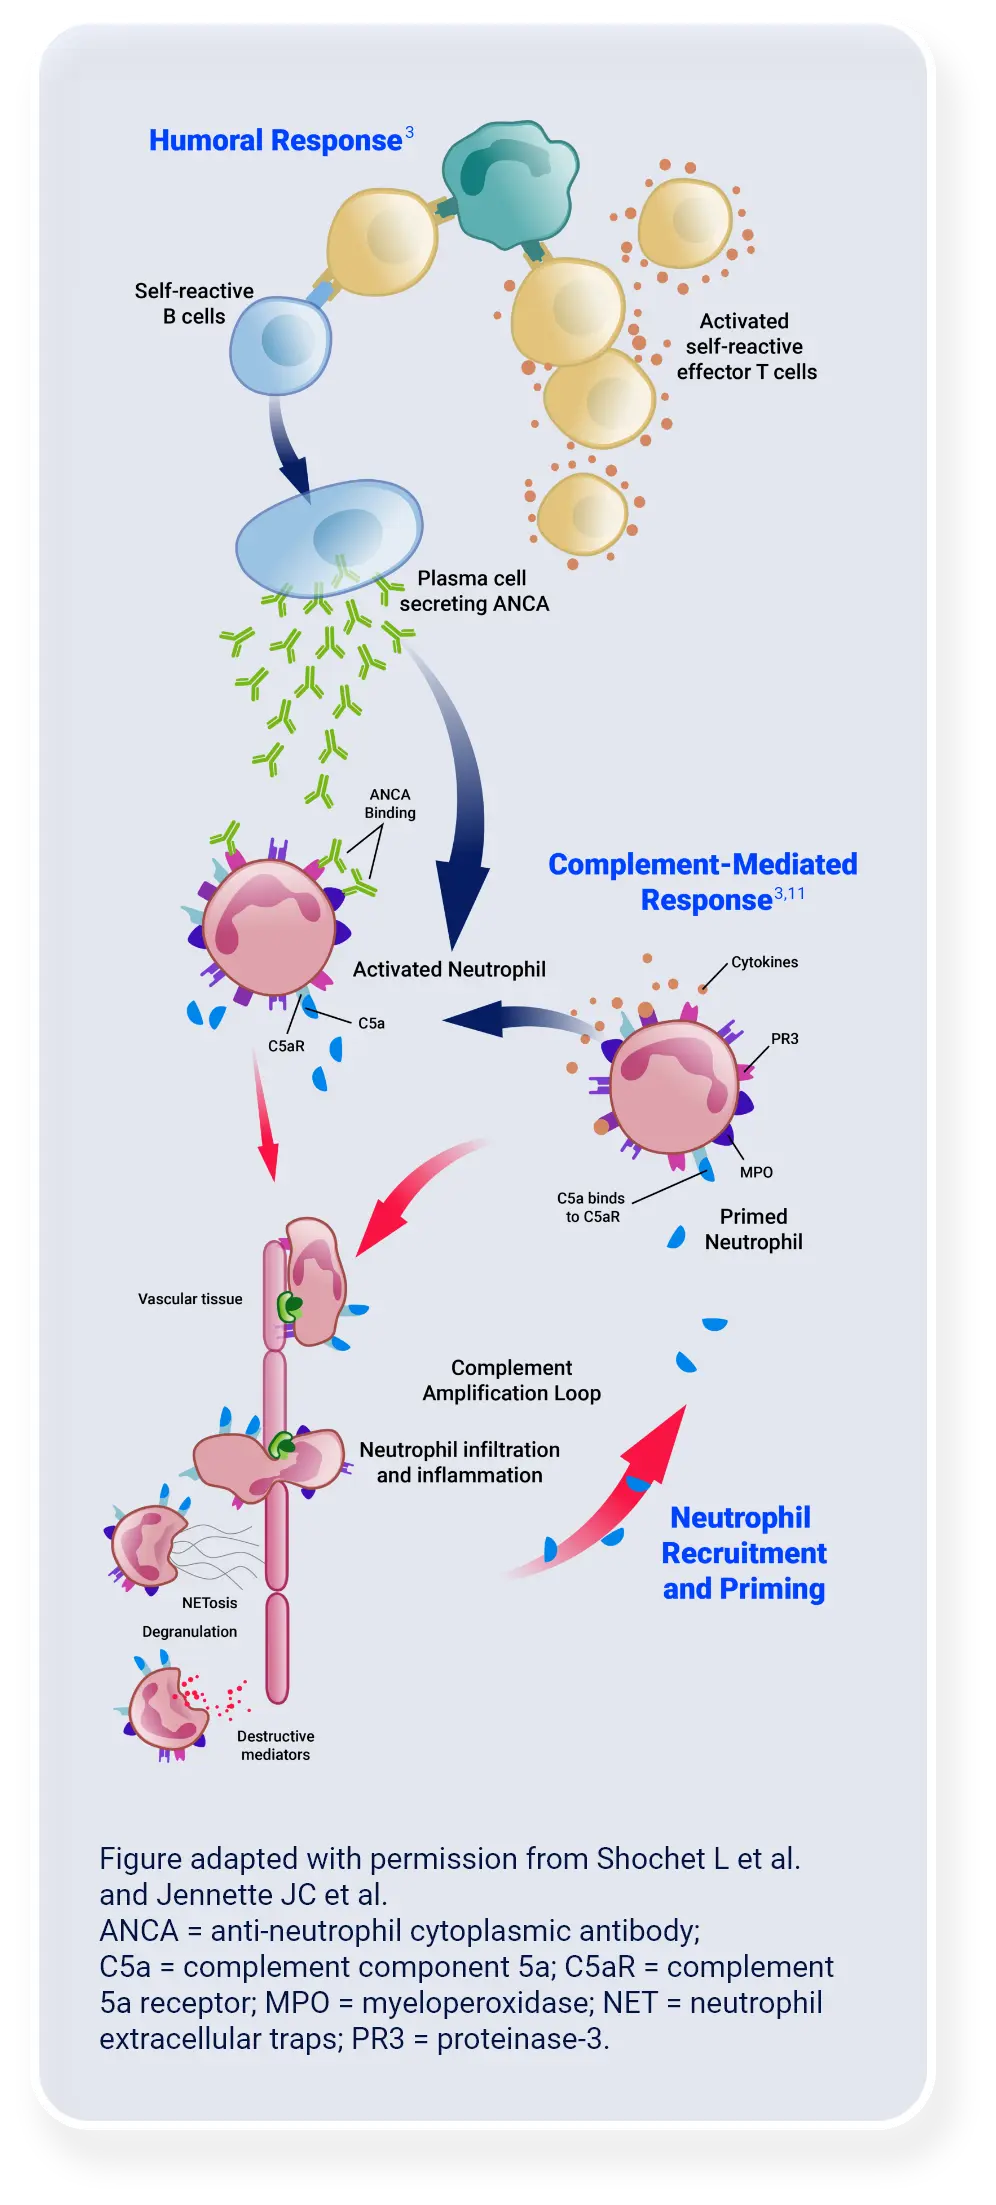
The interaction between C5a and one of its receptors, C5aR, plays a critical role in amplifying inflammation and vascular injury in GPA and MPA.3-5
Sudden visual loss, uveitis, blurred vision, scleritis, episcleritis, conjunctivitis, blepharitis, keratitis, retinal changes, significant proptosis, mouth ulcers, genital ulcers, adnexal inflammation8,12

Conductive hearing loss, sensorineural hearing loss8,12
Bloody nasal discharge, crusts, ulcers, granulomata, paranasal sinus involvement, subglottic stenosis8,12
Loss of pulses, valvular heart disease, pericarditis, ischemic cardiac pain, cardiomyopathy, congestive cardiac failure8,12
Wheezing, nodules or cavities, pleural effusion, pleurisy, infiltrates, endobronchial involvement, massive hemoptysis, alveolar hemorrhage, respiratory failure8,12
Peritonitis, bloody diarrhea, ischemic abdominal pain8,12
Hypertension, proteinuria, hematuria, changes in serum creatinine and creatinine clearance8,12
Infarct, purpura, ulcer, gangrene, other skin vasculitis8,12
Headache, meningitis, seizures, cerebrovascular accident, organic confusion, spinal cord lesion, cranial nerve palsy, sensory peripheral neuropathy, mononeuritis multiplex8,12

Myalgia, arthralgia, arthritis, fever, weight loss8,12
Please note these are just some of the signs and symptoms of severe active GPA or MPA. Severe active GPA or MPA can present differently in each patient.

A detailed history and physical examination are key to disease management13
Due to the multisystemic nature of GPA and MPA, awareness of signs/symptoms of disease activity across all organ systems is important for diagnosis2,14

While a positive ANCA result can provide additional support for diagnosis, up to 20% of patients with GPA and MPA are ANCA-negative15
A positive ANCA can also be found in other conditions without associated vasculitis such as autoimmune hepatitis, ulcerative colitis, hepatitis C, HIV, or infectious endocarditis15
Serology alone cannot be used to diagnose GPA or MPA14
Biopsy can be confirmatory, but treatment should not necessarily be delayed simply to get a biopsy2,15
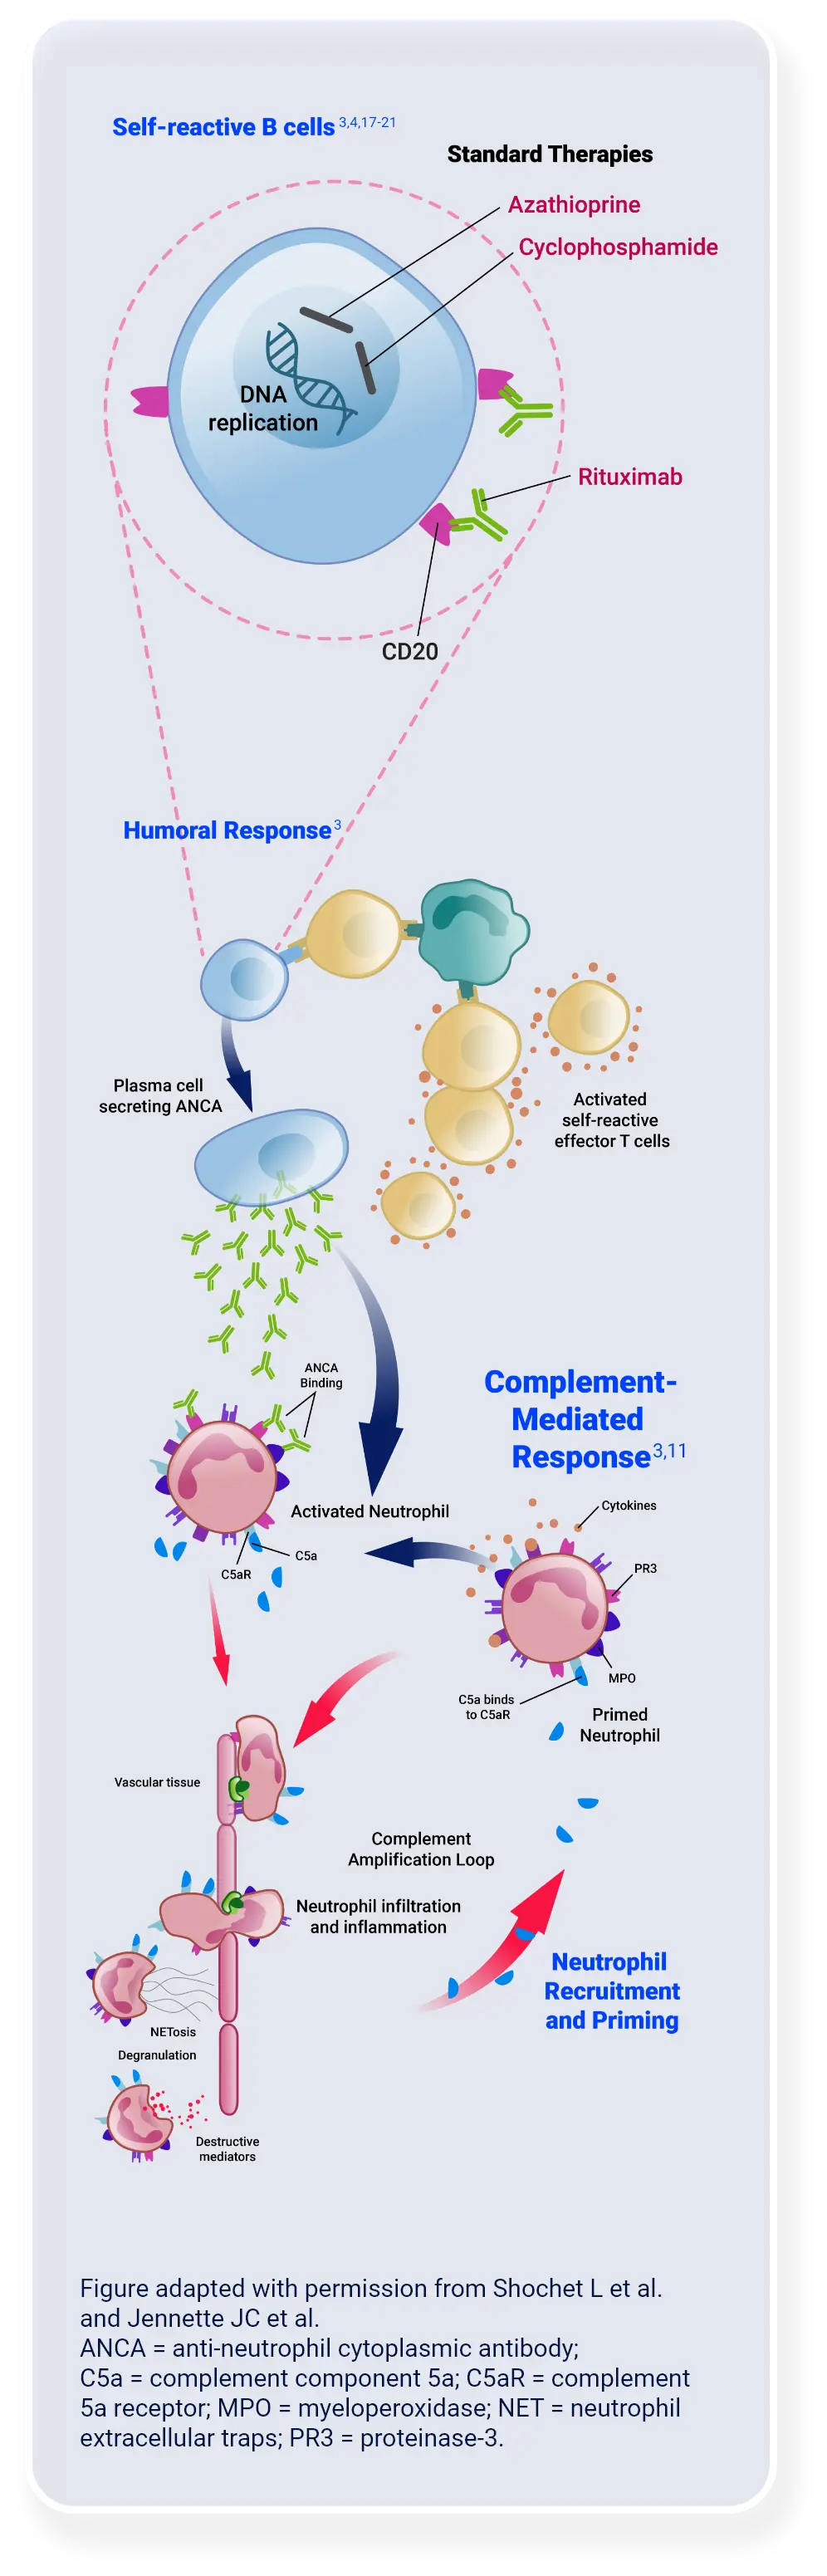
Opportunities to further care may start with understanding the humoral and complement mediated pathway of GPA and MPA pathophysiology6,16
About one-third of patients experience a significant diagnostic delay of more than 6 months1
Though many patients show renal disease, presenting manifestations can stretch across multiple organ systems2
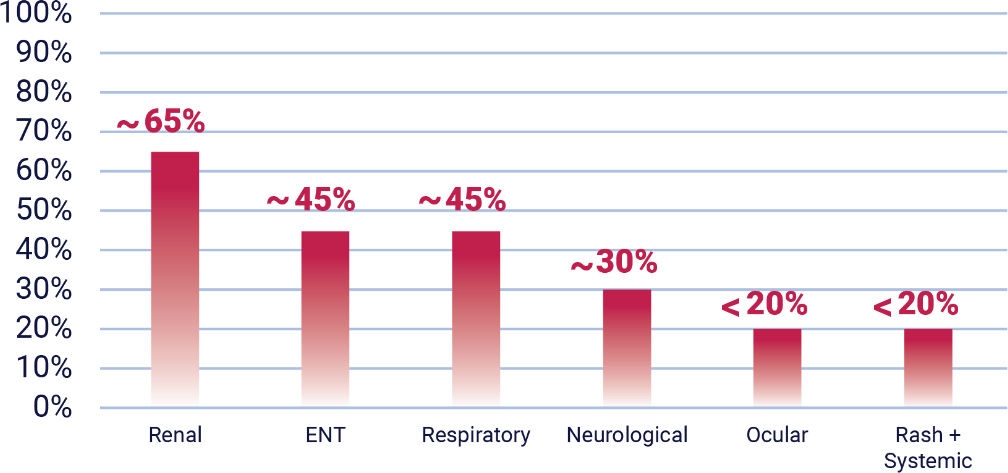
Though many patients show renal disease, presenting manifestations can stretch across multiple organ systems2
Presence of common comorbidities (>6%) may further complicate diagnosis3
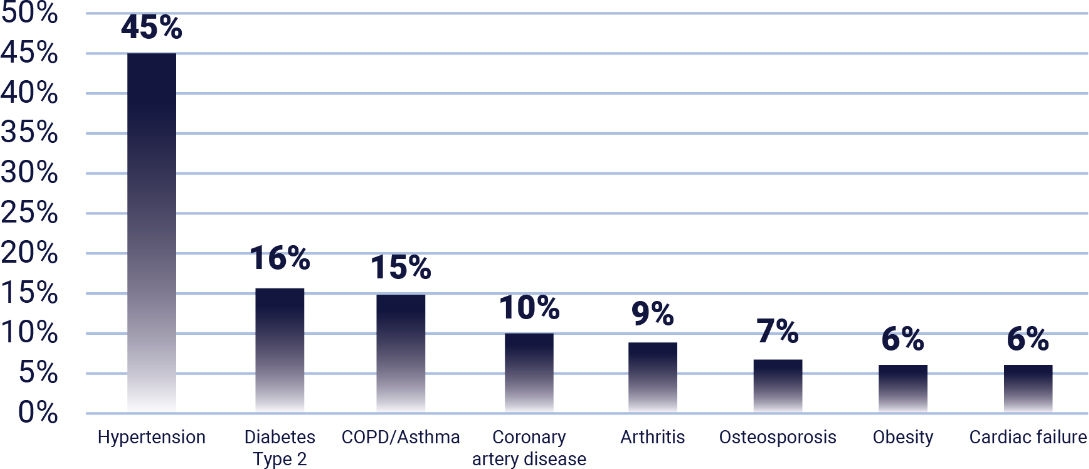
Presence of common comorbidities (>6%) may further complicate diagnosis3
As a result, 16% of patients have had their referral symptoms for approximately 3 months before receiving their diagnosis3
COPD = chronic obstructive pulmonary disease; ENT = ear, nose, throat.
Diagnosis requires a careful, systematic approach that can identify multi-organ system involvement.1
References: 1. Yates M, Watts R. Clin Med (Lond). 2017;17(1):60-64. 2. Hunter RW, Welsh N, Farrah TE, et al. BMJ. 2020;369:m1070. 3. Rutherford P, Goette D. Poster presented at: World Congress of Nephrology 2020; March 26-29, 2020; Abu Dhabi, United Arab Emirates. Abstract SUN-375.
Response to induction therapy is variable and many patients do not achieve full clinical remission (defined as a BVAS score of 0 with the patient off glucocorticoids)1
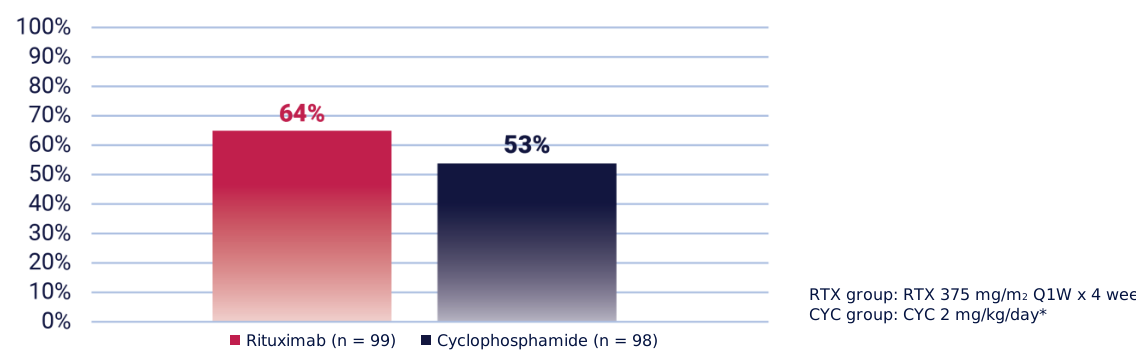
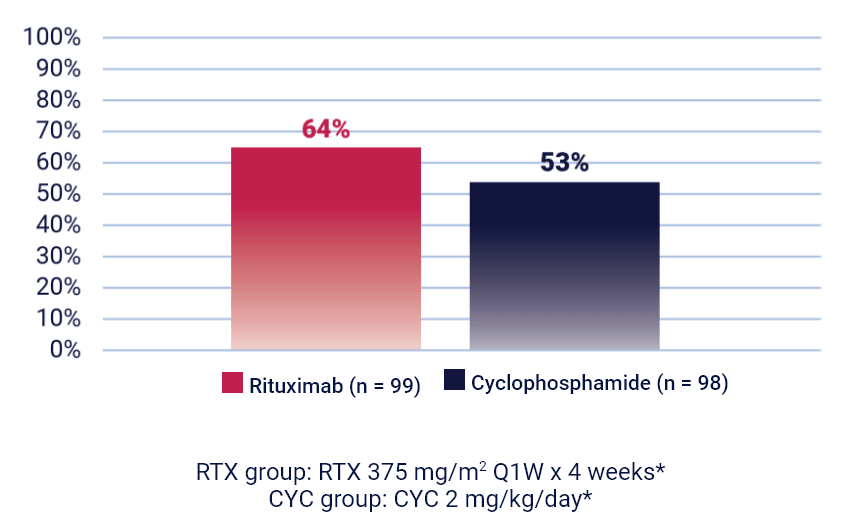
*Received one to three pulses of methylprednisolone (1000 mg each) followed by prednisone 1 mg/kg/day.
BVAS = Birmingham Vasculitis Activity Score; CYC = cyclophosphamide; Q1W = weekly; RTX = rituximab.
Reference: 1. Stone JH, Merkel PA, Spiera R, et al. N Engl J Med. 2010;363(3):221-232.
MAINRITSAN-11,2
N = 115 patients with GPA or MPA in complete remission (BVAS = 0) after combined glucocorticoids and “pulse” intravenous CYC
AZA arm (n = 58) received:
2 mg/kg/day until month 12
1.5 mg/kg/day until month 18
1 mg/kg/day until month 22
RTX arm (n = 57) received:
500 mg on days 0 and 14, then months 6, 12, and 18
Prednisone treatment:
Major relapse: reappearance or worsening of disease with BVAS >0 and involvement of at least one major organ, a life-threatening manifestation, or both.
Minor relapse: reappearance or worsening of disease with BVAS >0, not corresponding to a major relapse but requiring mild treatment intensification.
MAINRITSAN-1 Relapse Rates1
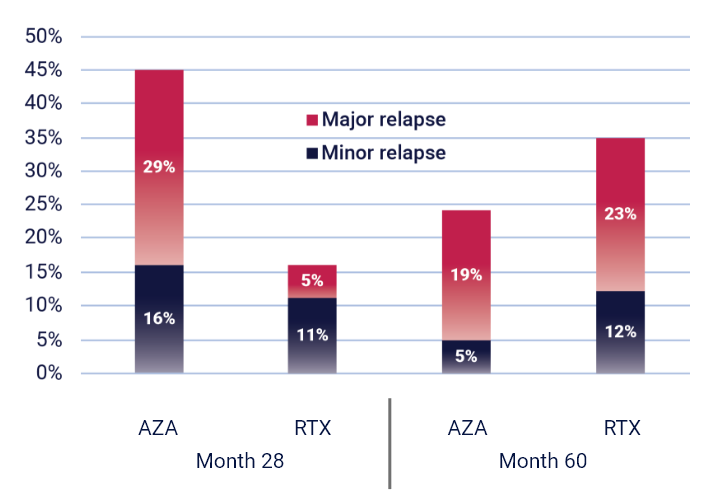
*Prednisone dose tapering and the decision to stop prednisone after month 18 were left to each site investigator’s discretion.
AZA = azathioprine; BVAS = Birmingham Vasculitis Activity Score; CYC = cyclophosphamide; RTX = rituximab.
Patients do still experience relapse when receiving therapy, and as a result, many still receive glucocorticoids long term1,3
References: 1. Terrier B, Pagnoux C, Perrodeau E, et al; French Vasculitis Study Group.em Ann Rheum Dis. 2018;77(8):1151-1157. 2. Guillevin L, Pagnoux C, Karras A, et al; French Vasculitis Study Group. N Engl J Med. 2014;371(19):1771-1780. 3. Miloslavsky EM, Specks U, Merkel PA, et al. Arthritis Rheumatol. 2015;67(6):1629-1636.
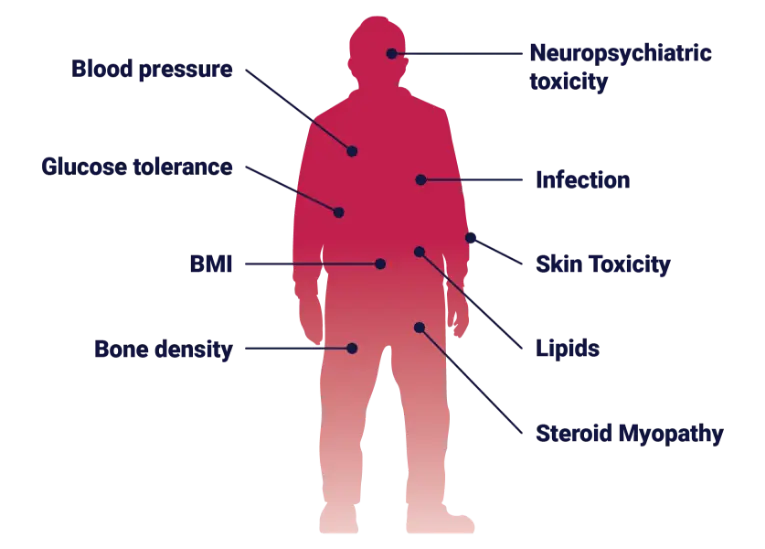
Even at lower doses, glucocorticoids can be associated with substantial morbidity1-3
Patients receiving glucocorticoid therapy for >6 months have a significantly greater incidence of infections (vs patients not using glucocorticoids after 6 months)*
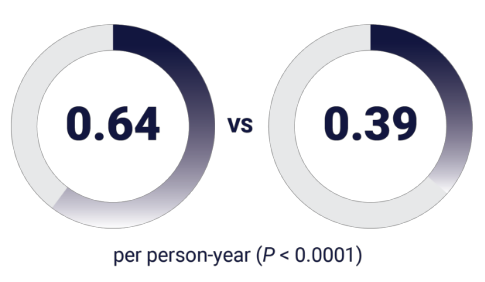
*Patients (N = 147) enrolled in the ANCA disease registry of the GDCN, with an initial diagnosis between 2000 and 2009, and remission on or off therapy attained for at least 1 month.
BMI = body mass index; GDCN = Glomerular Disease Collaborative Network.
References: 1. Pujades-Rodriguez M, Morgan AW, Cubbon RM, et al. PLoS Med. 2020;17(12):e1003432. 2. McGregor JG, Hogan SL, Hu Y, et al. Clin J Am Soc Nephrol. 2012;7(2):240-247. 3. Waljee AK, Rogers MAM, Lin P, et al. BMJ. 2017;357:j1415. 4. Stone JH, McDowell PJ, Jayne DRW, et al. The glucocorticoid toxicity index: measuring change in glucocorticoid toxicity over time. Semin Arthritis Rheum. 2022;55:152010.
Renal impairment is common with many patients1,2
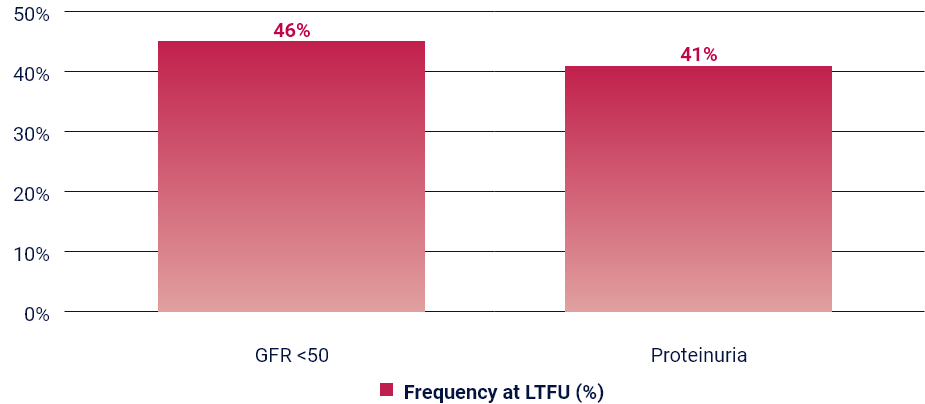
GFR = glomerular filtration rate; LTFU = long-term follow-up.
Reference: 1. Robson J, Doll H, Suppiah R, et al. Rheumatology (Oxford). 2015;54(3):471-481. 2. Robson J, Doll H, Suppiah R, et al. Ann Rheum Dis. 2015;74:177-184.
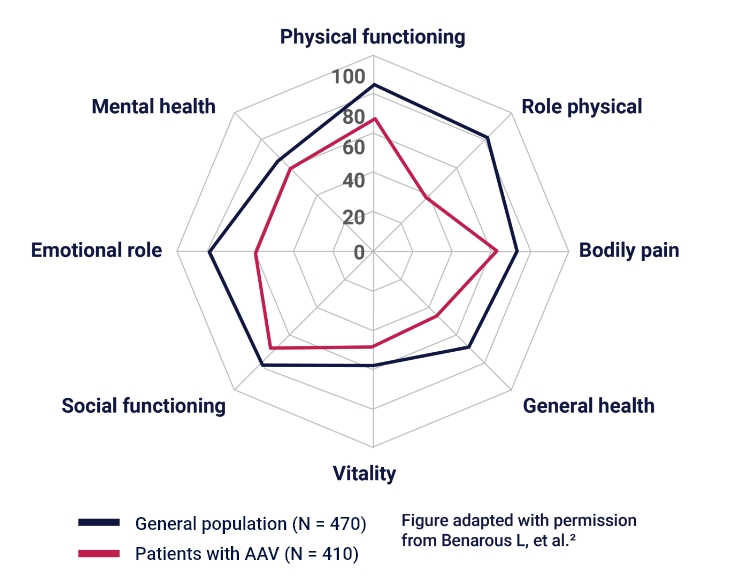
AAV = ANCA-associated vasculitis; QoL = quality of life.
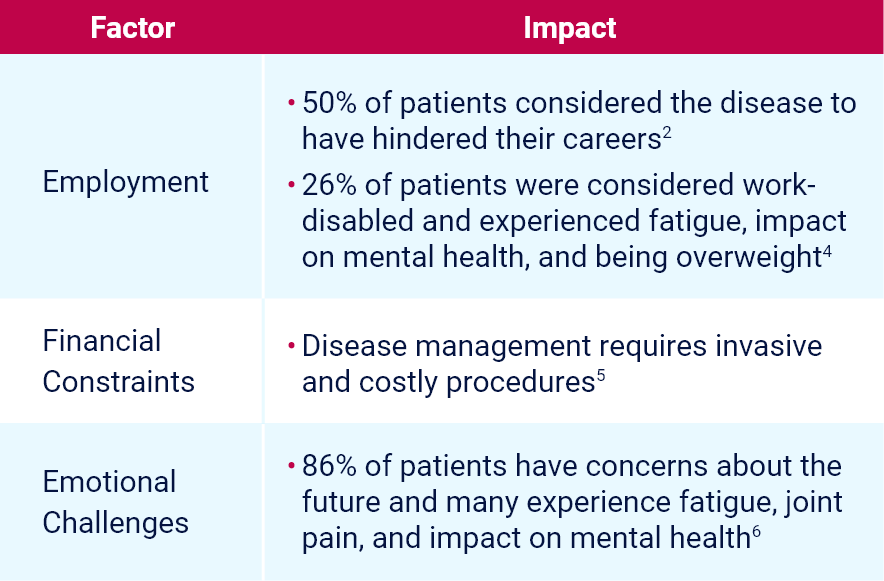
References: 1. Basu N, Jones GT, Fluck N, et al. Rheumatology (Oxford). 2010;49(7):1383-1390. 2. Benarous L, Terrier B, Laborde-Casterot H, et al. Clin Exp Rheumatol. 2017;35(suppl 103):40-46. 3. Basu N, McClean A, Harper L, et al. Ann Rheum Dis. 2014;73(1):207-211. 4. Basu N, McClean A, Harper L, et al. Rheumatology (Oxford). 2014;53(5):953-956. 5. Raimundo K, Farr AM, Kim G, et al. J Rheumatol. 2015;42(12):2383-2391. 6. Robson JC, Dawson J, Cronholm PF, et al. Patient Relat Outcome Meas. 2018;9:17-34.
Click the icons below to learn more about the potential challenges healthcare professionals face when treating severe active GPA and MPA.
– Brandon, living with GPA
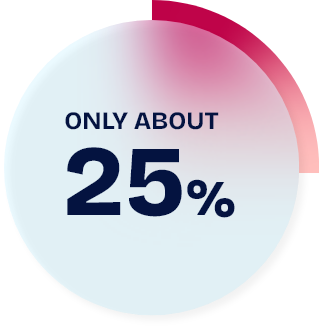

*According to an online, self-administered survey of 100 patients with GPA or MPA from July 21-August 25, 2022.
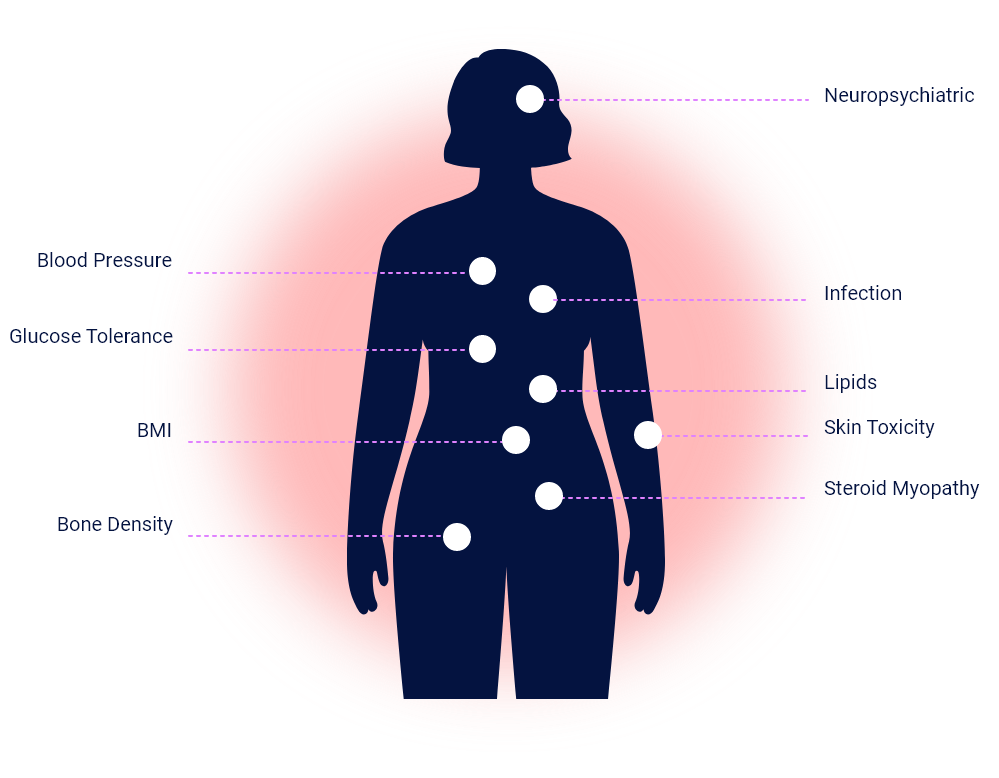
BMI = Body Mass Index.
– Brandon, living with GPA
Open conversation between a patient and their HCP is crucial when it comes to treating conditions like severe active GPA or MPA, as each may have different expectations of what successful treatment looks like.27,30 Here we’ve provided some useful topics to help you get the most out of these conversations with your patient.
Your patients may have symptoms that impact their ability to communicate effectively with you, including hearing loss.8 Be sure to consider your patient’s abilities when talking with them, such as facing your patient so they can fully understand you and so that you are both able to read each other’s body language.
What response is your patient hoping to achieve from their treatment?
When does your patient expect to start seeing results from their treatment?
Has your patient’s quality of life improved or worsened since they started treatment?
If your patient could change one thing about their current treatment, what might it be?
Does your patient understand what GPA or MPA are and the effects it may be having on their body?
Help ensure your patient is aware of the potential side effects that could arise from their current treatment regimen
Watch a national broadcast Amgen® put together around opportunities to further care in AAV, with a focus on GPA and MPA.

ANCA101 Education Resource
This resource provides a summary of the ANCA-associated vasculitis disease mechanism, severe active GPA and MPA manifestations, and challenges with management.
The following organizations provide education, support, and resources that may help your patient throughout their treatment journey.

The Vasculitis Foundation supports, inspires, and empowers people and families living with vasculitis through a wide range of education, research, clinical, and awareness initiatives.
Visit them at vasculitisfoundation.org

NORD (National Organization for Rare Disorders) is a patient advocacy organization committed to the identification, treatment, and cure of rare disorders through programs of education, advocacy, research, and patient services.
Visit them at rarediseases.org

The American Kidney Fund (AKF) works on behalf of Americans living with and at risk of kidney disease, with programs that support people from prevention through transplant and beyond.
Visit them at kidneyfund.org
1. Tekin Mİ, Özdal MPC. Acta Medica. 2021;52(4):257-263.
2. Yates M, Watts R. Clin Med (Lond). 2017;17(1):60-64.
3. Shochet L, Holdsworth S, Kitching AR. Front Immunol. 2020;11:525.
4. Kitching AR, Anders H-J, Basu N, et al. Nat Rev Dis Primers. 2020;6(1):71.
5. Al-Hussain T, Hussein MH, Conca W, Al Mana H, Akhtar M. Adv Anat Pathol. 2017;24(4):226-234.
6. Jennette JC, Falk RJ, Bacon PA, et al. Arthritis Rheum 2013;65(1):1-11. doi: 10.1002/art.37715
7. Langford C. Cleve Clin J Med. 2012;79(suppl3):S3-15.
8. Supplement to: Jayne DRW, Merkel PA, Schall TJ, Bekker P; ADVOCATE Study Group. N Engl J Med. 2021;384(7):599-609.
9. Chung SA, Langford CA, Maz M, et al. Arthritis Rheumatol. 2021;73(8):1366-1383.
10. Lamprecht P, Kerstein A, Klapa S, et al. Front Immunol. 2018;9:1-10.
11. Jennette JC, Nachman PH. Clin J Am Soc Nephrol. 2017;12(10):1680-1691.
12. Mukhtyar CB. In: Watts RA, Scott DGI, eds. Vasculitis in Clinical Practice. Springer; 2010:13-19.
13. Qasim A, Patel JB. In: StatPearls [Internet]. StatPearls Publishing; 2023. Accessed October 3, 2023. https://www.ncbi.nlm.nigh.bov/books/NBK554372/
14. Hunter RW, Welsh N, Farrah TE, et al. BMJ. 2020;369:m1070.
15. Pagnoux C. Eur J Rheumatol. 2016;3(3):122-133.
16. Chen M, Jayne DRW, Zhao M-H. Nat Rev Nephrol. 2017;13(6):359-367.
17. Jones RB, Ferraro AJ, Chaudhry AN, et al. Arthritis Rheum. 2009;60(7):2156-2168.
18. Winkelstein A. Blood. 1973;41(2):273-284.
19. Eickenberg S, Mickholz E, Jung E, et al. Arthritis Res Ther. 2012;14(3):R110.
20. Ogino MH, Prasanna T. In: StatPearls [Internet]. StatPearls Publishing; 2023. Accessed October 3, 2023. https://www.ncbi.nlm.nigh.bov/books/NBK5553087/
21. Mohammadi O, Kassim TA. In: StatPearls [Internet]. StatPearls Publishing; 2023.
22. Stone JH, Merkel PA, Spiera R, et al; RAVE-ITN Research Group. N Engl J Med. 2010;363(3):221-232.
23. Terrier B, Pagnoux C, Perrodeau E, et al; French Vasculitis Study Group. Ann Rheum Dis. 2018;77(8):1151-1157.
24. Stone JH, McDowell PJ, Jayne DRW, et al. Semin Arthritis Rheum. 2022;55:152010
25. King C, Harper L. Current Treatment Options in Rheumatology. 2017;3(4):230-243. doi.org/10.1007/s40674-017-0082-y
26. Robson J, Doll H, Suppiah R, et al. Rheumatology (Oxford). 2015;54(3):471-481.
27. Robson JC, Dawson J, Cronholm PF, et al. Patient Relat Outcome Meas. 2018;9:17-34.
28. Jayne DRW, Merkel PA, Schall TJ, Bekker P; ADVOCATE Study Group. N Engl J Med. 2021;384(7):599-609.
29. Neumann I. Rheumatology (Oxford). 2020;59(suppl 3):iii60-iii67.
30. Data on file, Amgen; Harris Poll [91973]; 2022.
31. Furuta S, Nakagomi D, Kobayashi Y, et al. JAMA. 2021;325(21):2178-2187.